
Form Cms L564 Printable
Form Cms L564 Printable - Use this form to show proof of group health plan coverage based on current employment so you can enroll in medicare. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. The valid omb control number for this. If you are applying during the special enrollment period, also fill out the request for employment. This form is used for proof of group health care coverage based on current employment. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. You can electronically complete, upload, and submit select forms to social. This guide will provide you with clear and supportive instructions on completing the form online. This information is needed to process your medicare enrollment application. You complete section a of this form, then ask your employer to fill out section b. Use this form to show proof of group health plan coverage based on current employment so you can enroll in medicare. If you are applying during the special enrollment period, also fill out the request for employment. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search. This information is needed to process your medicare enrollment application. You complete section a of this form, then ask your employer to fill out section b. This guide will provide you with clear and supportive instructions on completing the form online. The purpose of this form is to provide documentation to social security that proves that you have been continuously. This information is needed to process your medicare enrollment application. If you are applying during the special enrollment period, also fill out the request for employment. You can electronically complete, upload, and submit select forms to social. You complete section a of this form, then ask your employer to fill out section b. Use this form to show proof of. The valid omb control number for this. Use this form to show proof of group health plan coverage based on current employment so you can enroll in medicare. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more. This guide will provide you with clear and supportive instructions on completing the form online. You can electronically complete, upload, and submit select forms to social. This information is needed to process your medicare enrollment application. You complete section a of this form, then ask your employer to fill out section b. Use this form to show proof of group. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. This form is used for proof of group health care coverage based on current employment. You complete section a of this form, then ask your employer to fill out section b. Use this form to show proof of group. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. Use this. You can electronically complete, upload, and submit select forms to social. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. Use this form to show proof of group health plan coverage based on current employment. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. This form is used for proof of group health care coverage based on current employment. You complete section a of this form, then ask your employer to fill out section b. The purpose of this form is to provide. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more. Use this form to show proof of group health plan coverage based on current employment so you can enroll in medicare. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. This form is used for proof of group health care coverage. The valid omb control number for this. This guide will provide you with clear and supportive instructions on completing the form online. This form is used for proof of group health care coverage based on current employment. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. The time. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. You complete section a of this form, then ask your employer to fill out section b. This form is used for proof of group health care coverage based on current. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. You can electronically complete, upload, and submit select forms to social. If you are applying during the special enrollment period, also fill out the request for. You can electronically complete, upload, and submit select forms to social. If you are applying during the special enrollment period, also fill out the request for employment. You complete section a of this form, then ask your employer to fill out section b. This information is needed to process your medicare enrollment application. Use this form to show proof of. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources,. This information is needed to process your medicare enrollment application. Use this form to show proof of group health plan coverage based on current employment so you can enroll in medicare. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. Use. If you are applying during the special enrollment period, also fill out the request for employment. This form is used for proof of group health care coverage based on current employment. This guide will provide you with clear and supportive instructions on completing the form online. The time required to complete this information collection is estimated to average 15 minutes. This form is used for proof of group health care coverage based on current employment. The valid omb control number for this. You can electronically complete, upload, and submit select forms to social. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer. The valid omb control number for this. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. You complete section a of this form, then ask your employer to fill out section b. If you are applying during the special. This guide will provide you with clear and supportive instructions on completing the form online. You complete section a of this form, then ask your employer to fill out section b. Use this form to show proof of group health plan coverage based on current employment so you can enroll in medicare. Use this form to show proof of group. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. You complete section a of this form, then ask your employer to fill out section b. If you are applying during the special enrollment period, also fill out the request. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. This form is used for proof of group health care coverage based on current employment. Use this form to show proof of group health plan coverage based on current employment so you. This information is needed to process your medicare enrollment application. If you are applying during the special enrollment period, also fill out the request for employment. This form is used for proof of group health care coverage based on current employment. This guide will provide you with clear and supportive instructions on completing the form online. If you cannot find. If you are applying during the special enrollment period, also fill out the request for employment. This guide will provide you with clear and supportive instructions on completing the form online. This information is needed to process your medicare enrollment application. You complete section a of this form, then ask your employer to fill out section b. Use this form. You can electronically complete, upload, and submit select forms to social. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. The valid omb control number for this. This form is used for proof of group health care coverage based on current. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. This information is needed to process your medicare enrollment application. The time required to complete this information collection is estimated to average 15 minutes per response,. You complete section a of this form, then ask your employer to fill out section b. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. This guide will provide you with clear and supportive instructions on completing the form online. Use. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. This information is needed to. This information is needed to process your medicare enrollment application. You can electronically complete, upload, and submit select forms to social. This guide will provide you with clear and supportive instructions on completing the form online. If you are applying during the special enrollment period, also fill out the request for employment. Use this form to show proof of group. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. This information is needed to. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. This information is needed to process your medicare enrollment application. You can electronically complete, upload, and submit select forms to social. You complete section a of this form, then ask your employer. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. This guide will provide you with clear and supportive instructions on completing the form online. If you cannot find the form you need or require assistance completing the form, please. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. Use this form to show proof of group health plan coverage based on current employment for medicare enrollment by completing section a yourself and having your employer fill out section. This form. If you are applying during the special enrollment period, also fill out the request for employment. The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the. If you cannot find the form you need or require assistance completing the form, please go to the contact us link. The purpose of this form is to provide documentation to social security that proves that you have been continuously covered by a group health plan based on current employment, with no more than 8. You complete section a of this form, then ask your employer to fill out section b. You can electronically complete, upload, and submit select forms to social. The valid omb control number for this. This form is used for proof of group health care coverage based on current employment. This information is needed to process your medicare enrollment application.
The Medicare Form CMSL564 for Employers
Medicare Part B Application Form Cms L564 Form Resume Examples
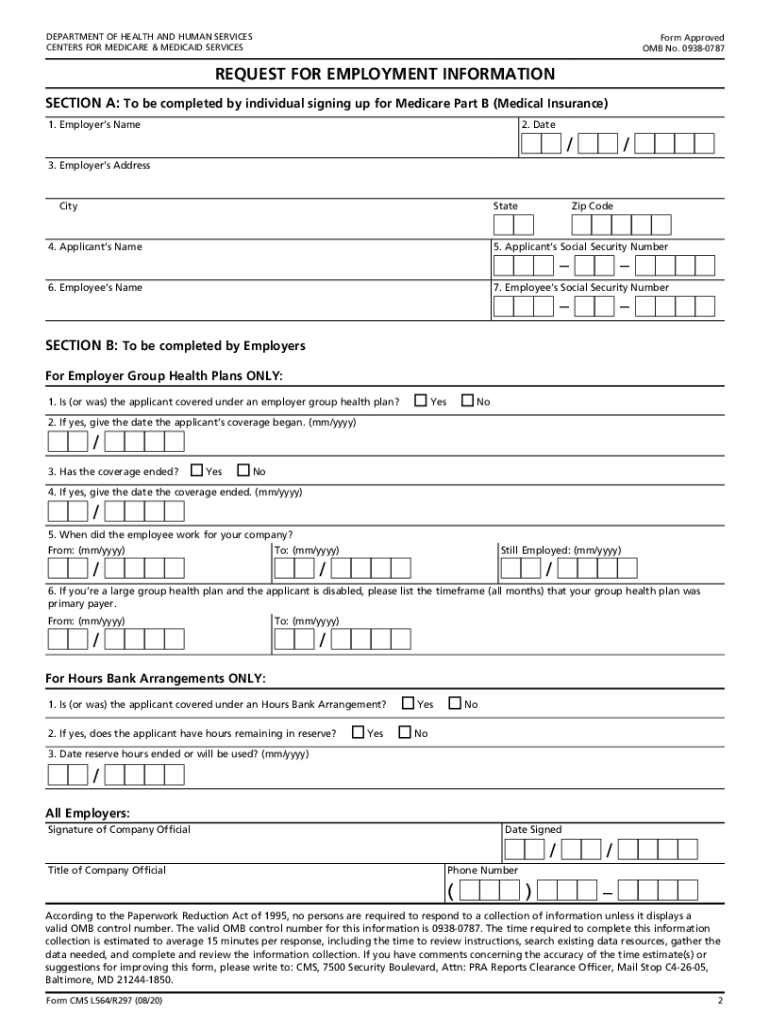
Printable Form Cms L564 Cms R 297 Printable Forms Free Online

The Medicare Form CMSL564 for Employers

The Medicare Form CMSL564 for Employers

The Medicare Form CMSL564 for Employers

Request for Employment Information Form Blank Fillable Template
CMS 1500 Form 20252026 Fill, Edit and Download PDF Guru

2020 2023 Form Cms L564 Fill Online Printable Fillable Blank Pdffiller
CMS Form L564 Download Guide PDF

CMS L564 (HCFA L564) Form Download PDF + Complete Guide (2025)

CMS L564 Form Avoid Medicare Penalties Expert Guide 2025
Fill Form FS Form 5511 TreasuryDirect Transfer Request 20252026

Form CMS L564 Download Fillable PDF or Fill Online Request for

The Medicare Form CMSL564 for Employers

The Medicare Form CMSL564 for Employers
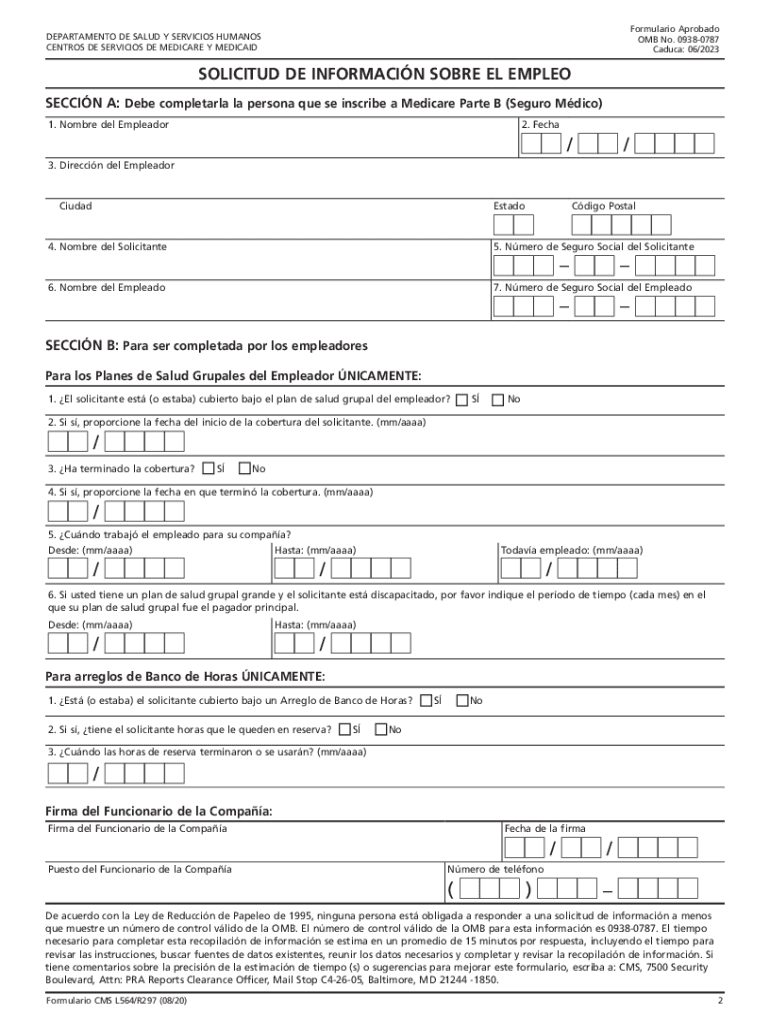
Ssa Form Cms L564 Printable Printable Forms Free Online

Form Cms L564 Fill Out and Sign Printable PDF Template airSlate SignNow

Fillable Form CmsL564 Request For Employment Information printable

Videos — Medicare Mindset, LLC
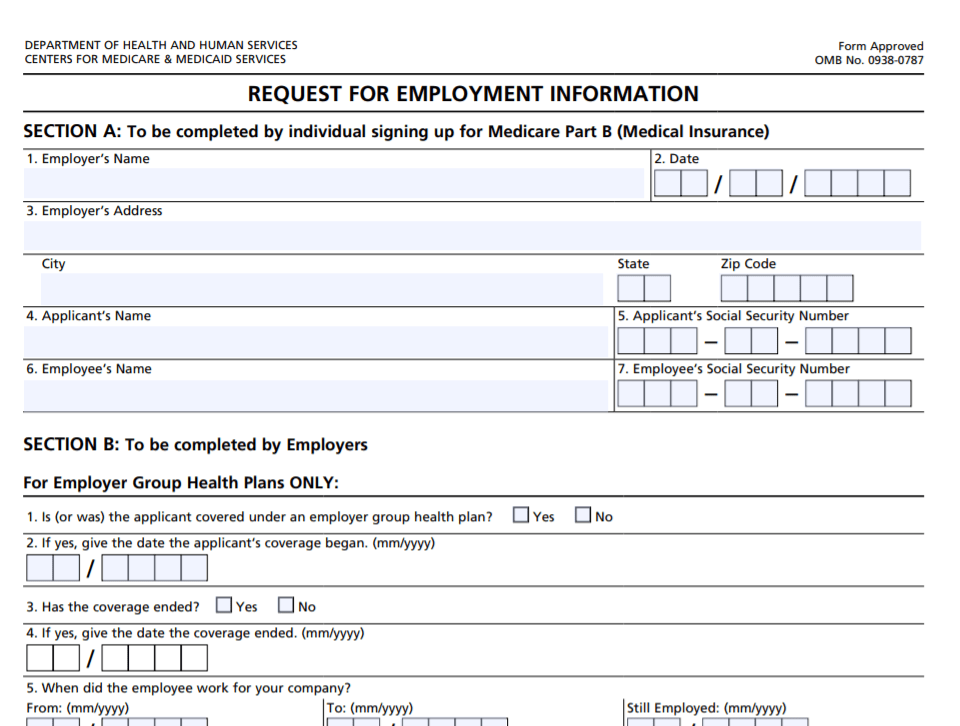
Form CMSL564 Request for Employment Information DocumentsHelper

Get Form CMS L564 Printable Easy Fill [PDF] Printables for Everyone

Form Cms L564 Printable Printable Free Templates

Cms L564 Printable Form Printable Free Templates

Get Form CMS L564 Printable Easy Fill [PDF] Printables for Everyone

CMS L564 Form 20252026 How to Fill and Edit PDF Guru

Agent Application Form Blank Fillable Template Fill Out, Print

The Medicare Form CMSL564 for Employers

The Medicare Form CMSL564 for Employers

Cms L564 Printable Form
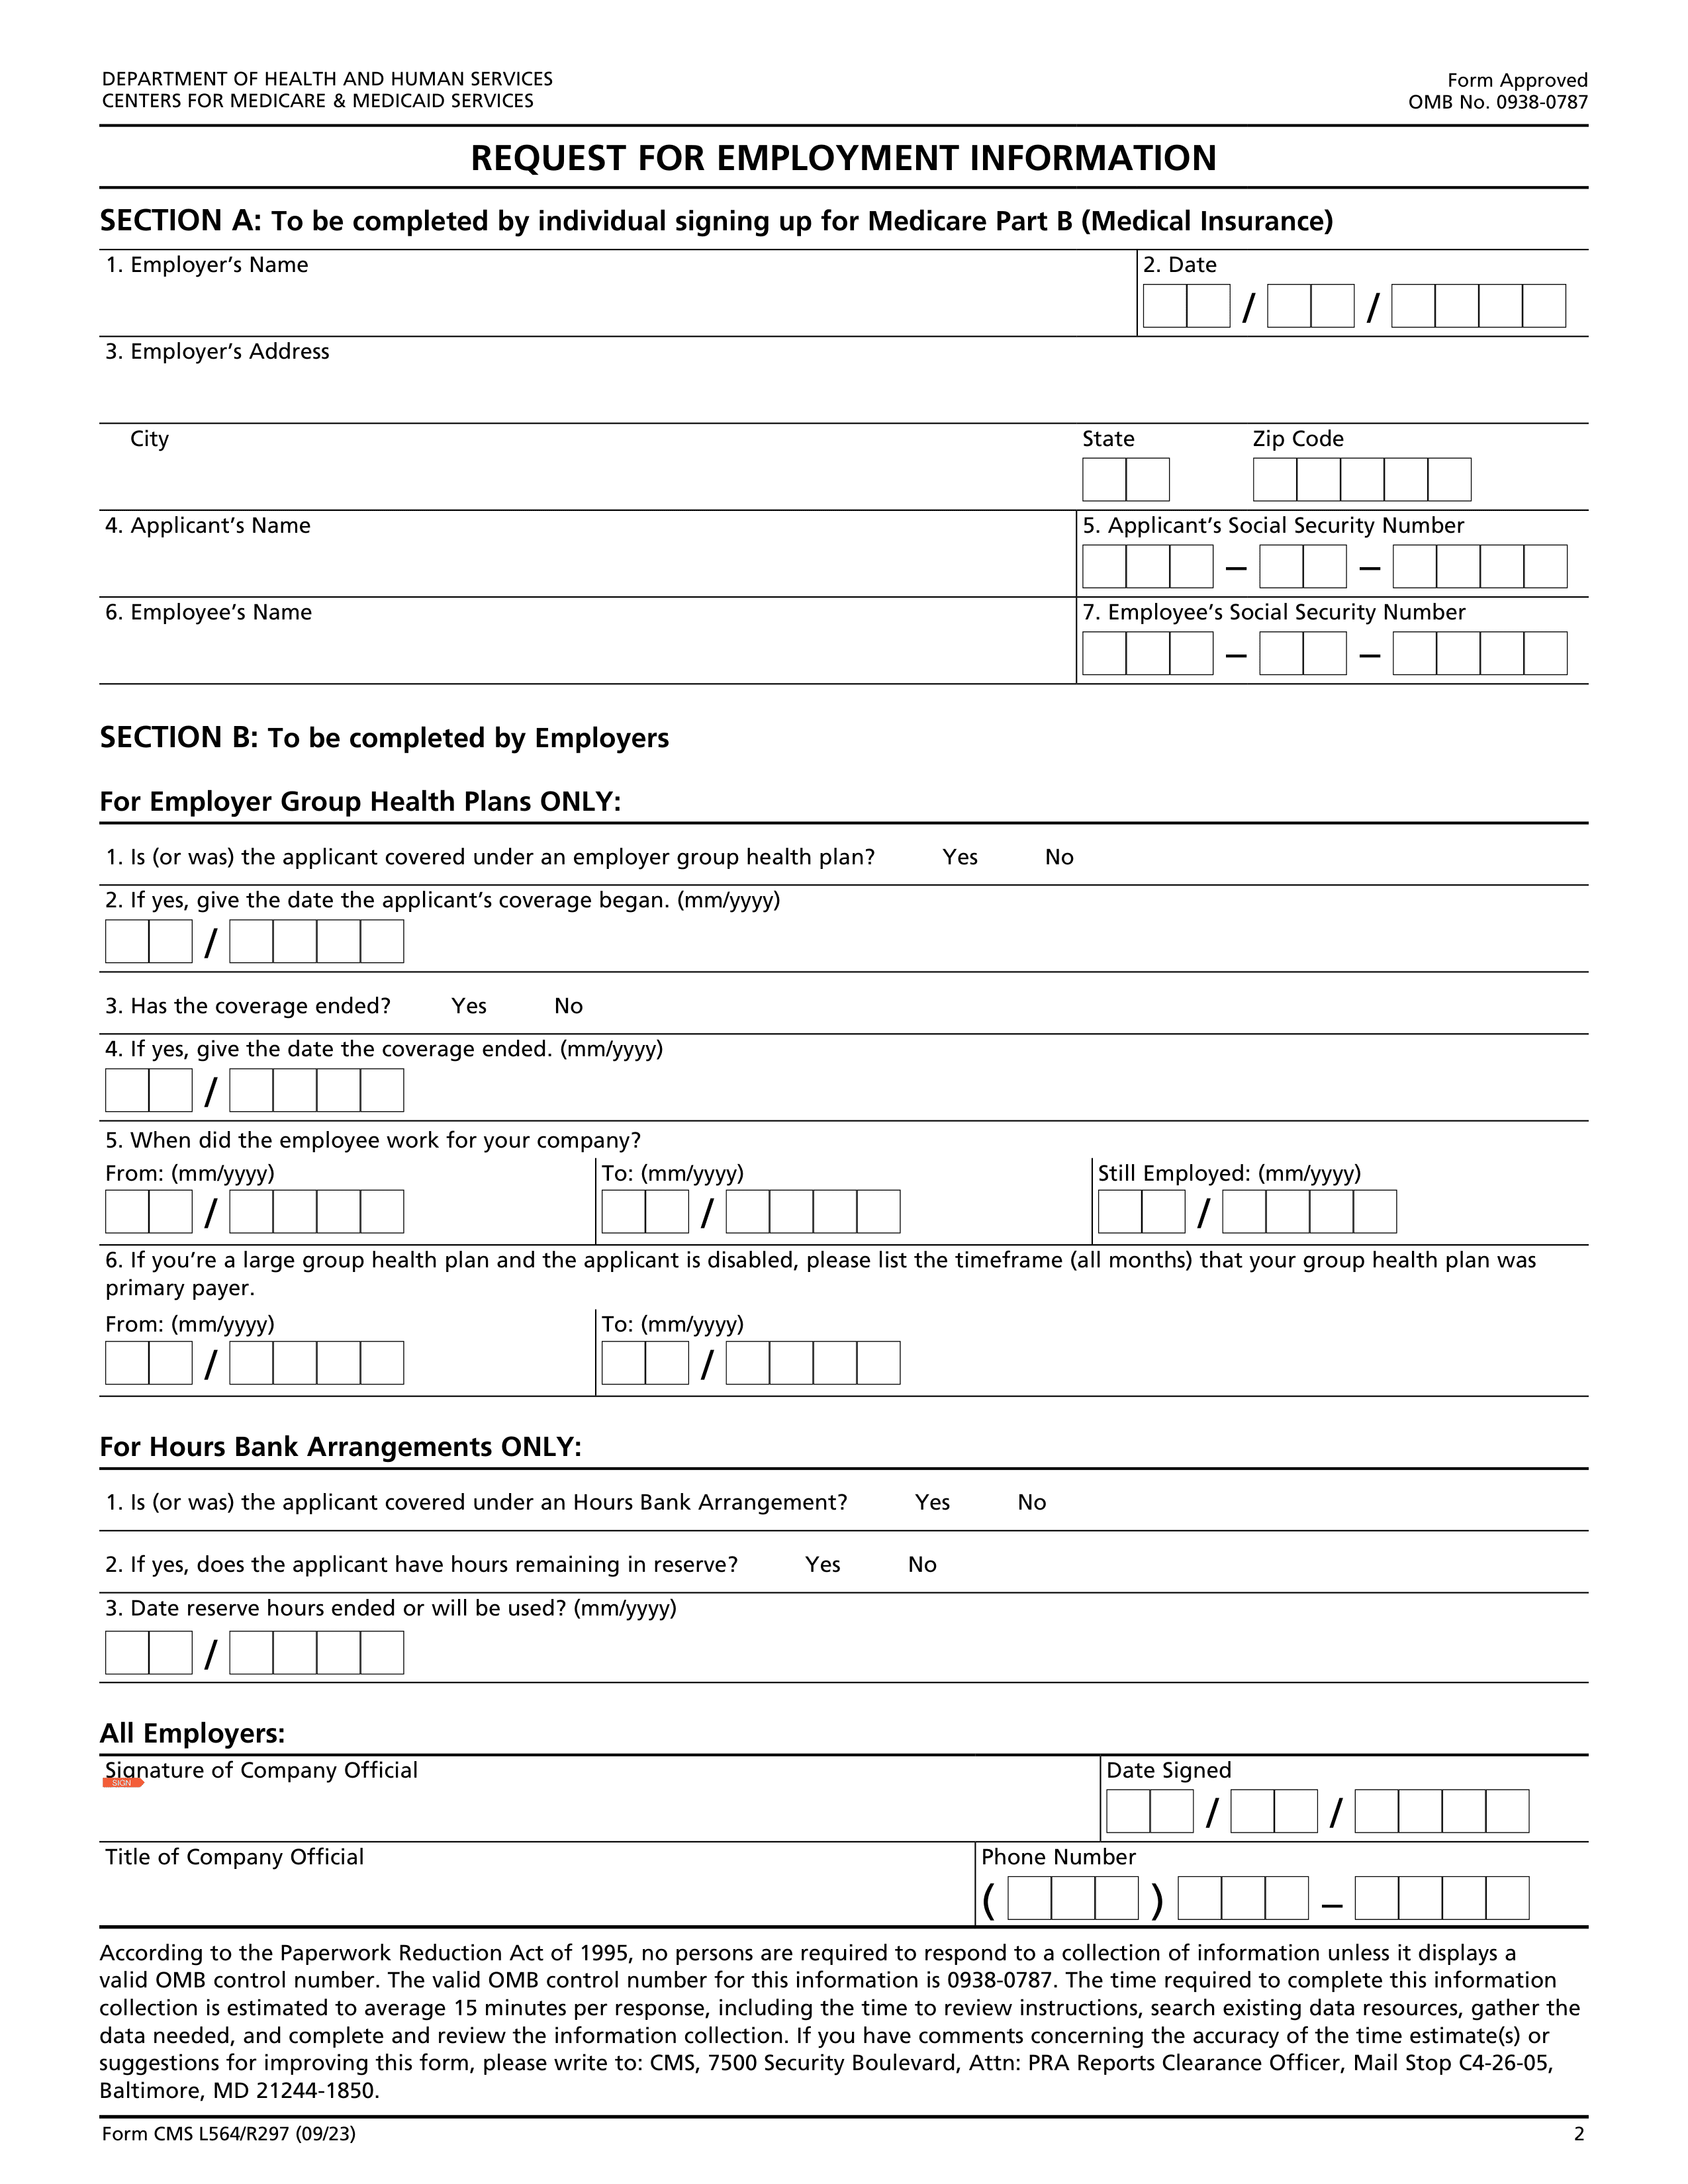
Form 8606 20252026 Fill, Edit, Download with PDF Guru

Cms L564 Printable Form Printable Free Templates

Easily Complete and Submit Medicare Form CMSl564 and CMS40B

The Medicare Form CMSL564 for Employers

Form Cms L564 Printable King Printables
This Guide Will Provide You With Clear And Supportive Instructions On Completing The Form Online.
Use This Form To Show Proof Of Group Health Plan Coverage Based On Current Employment For Medicare Enrollment By Completing Section A Yourself And Having Your Employer Fill Out Section.
Use This Form To Show Proof Of Group Health Plan Coverage Based On Current Employment So You Can Enroll In Medicare.
Related Post:
